
BACKGROUND AND AIMS
Brain metastases (BM) represent one of the most clinically significant complications of human epidermal growth factor receptor 2 (HER2)-positive metastatic breast cancer (MBC), affecting quality of life, treatment options, and survival. Tucatinib in combination with trastuzumab and capecitabine demonstrated substantial intracranial activity in the HER2CLIMB trial and established a new treatment paradigm for patients with HER2-positive MBC and central nervous system (CNS) involvement.1 Additional analyses have further confirmed the durable intracranial efficacy and survival benefit of tucatinib-based therapy in patients with HER2-positive MBC and BM.2
As systemic therapies improve extracranial disease control, the cumulative incidence of CNS progression continues to rise, with historical studies reporting a lifetime risk of CNS involvement approaching 30–50% in patients with HER2-positive disease.3 Earlier HER2-directed CNS studies similarly highlighted the persistent unmet need for more effective prevention and treatment strategies for BM.4
More recently, trastuzumab deruxtecan (T-DXd) demonstrated superior systemic efficacy and promising intracranial activity across the DESTINY-Breast clinical trials.5-7 Despite these advances, comparative real-world data evaluating the risk of developing incident BM among patients without baseline CNS disease remain limited.
MATERIALS AND METHODS
The authors conducted a retrospective cohort study using the TriNetX™ (TriNetX, LLC, Cambridge, Massachusetts, USA) federated electronic health record network.8 Eligible patients had HER2-positive MBC previously treated with first-line taxane, trastuzumab, and pertuzumab and had no documented BM before second-line treatment initiation. Patients receiving T-DXd or tucatinib, trastuzumab, and capecitabine (TTC) were included. Prior exposure to trastuzumab emtansine or pre-existing BM resulted in exclusion.
To minimize misclassification from occult baseline CNS disease, a landmark sensitivity analysis excluded events occurring within 60 days of treatment initiation. Cohorts were balanced using 1:1 propensity score matching based on age, comorbidity burden, and prior treatment exposure. The primary endpoint was incident BM. Secondary endpoints included BM-free survival, CNS-related morbidity, healthcare utilization, and overall survival.
RESULTS
After propensity score matching, 540 patients were included in each treatment cohort. Median follow-up was 13.4 months. Incident BM developed in 12.6% of patients treated with T-DXd compared with 20.9% of those receiving TTC, corresponding to a 38% relative risk reduction (risk ratio: 0.62; 95% CI: 0.46–0.83; p=0.0015). BM-free survival favored T-DXd, with 1-year BM-free survival rates of 72.7% versus 67.9% for TTC (hazard ratio: 0.72; 95% CI: 0.54–0.97; log-rank p=0.03; Table 1). Among patients who subsequently developed BM, those treated with TTC experienced a greater healthcare encounter burden, suggesting increased CNS-related clinical complexity.
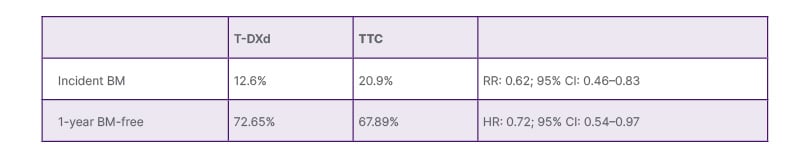
Table 1: BM outcomes in HER2+ MBC.
BM: brain metastases; HER2+: human epidermal growth factor receptor 2-positive; HR: hazard ratio; RR: risk ratio; T-DXd: trastuzumab deruxtecan; TTC: tucatinib, trastuzumab, and capecitabine.
Furthermore, CNS morbidity events, including seizures and cerebral edema, occurred less frequently among patients receiving T-DXd. Despite these differences in CNS outcomes, no statistically significant difference in overall survival was observed between treatment groups (hazard ratio: 0.89; 95% CI: 0.76–1.04; p=0.16).
CONCLUSION
In this real-world analysis of patients with HER2-positive MBC without baseline BM following first-line taxane, trastuzumab, and pertuzumab, treatment with T-DXd was associated with a significantly lower risk of developing incident BM and prolonged BM-free survival compared with tucatinib-based therapy. These findings complement prospective evidence demonstrating meaningful intracranial activity with T-DXd and support its emerging role in the management of CNS disease in HER2-positive MBC.5-7 The possibility that earlier use of T-DXd may modify CNS disease evolution warrants prospective validation using standardized CNS surveillance and biomarker-guided risk stratification strategies. The present findings extend prior CNS-focused HER2-directed therapy literature and provide real-world comparative evidence in a clinically relevant second-line population.8






