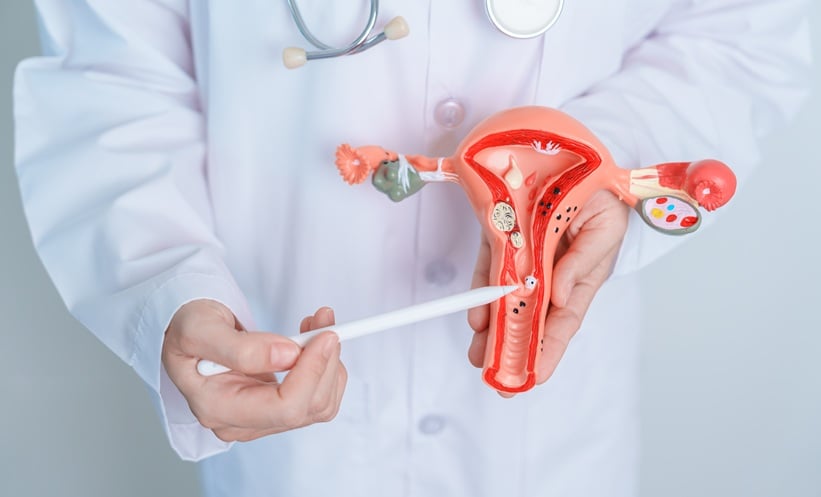
OVARIAN metastases from colorectal cancer may respond less well to chemotherapy than disease elsewhere, according to a narrative review published in JAMA Oncology.
The review covered 24 retrospective studies involving 2,705 patients. Better survival was associated with complete surgical removal, particularly when margins were microscopically clear. The findings favour considering surgery and systemic treatment together, while leaving uncertainty about how much surgery itself contributes to survival.
Different Responses Across Metastatic Sites
The authors found lower chemotherapy response rates and less shrinkage in ovarian lesions than in extraovarian metastases. Ovarian disease sometimes grew despite treatment controlling disease elsewhere.
They interpret this pattern as supporting the ovaries acting as a relative chemotherapy sanctuary. However, systemic treatment still has a role in controlling disease outside the ovaries and reducing the overall tumour burden.
Complete Resection Associated With Better Outcomes
The most favourable surgical outcomes were reported when metastatic disease was completely removed, with negative microscopic margins. The authors recommend considering ovarian surgery within comprehensive disease control, including treatment of the primary tumour, rather than as an isolated intervention.
This distinction matters when interpreting the findings. Removing an ovarian lesion and controlling a patient’s total cancer burden are different treatment objectives. A response at one anatomical site cannot, by itself, establish that all clinically important disease has been controlled.
Interpreting the Evidence Carefully
Because the studies were retrospective, the survival comparisons should be read as associations. Patients selected for surgery may differ from those receiving systemic treatment alone in ways that also affect prognosis. For example, a group with more readily removable disease is not automatically comparable with a group whose disease cannot be removed.
This is a question about how the evidence should be interpreted, rather than evidence that an operation is ineffective. Demonstrating that selected surgical patients live longer is different from establishing how long those same patients would have lived without surgery.
For clinicians reading the review, the practical distinction is between identifying a potentially useful treatment strategy and proving its additional benefit. The review provides a rationale for assessing disease at individual sites and considering whether complete removal is feasible. It does not provide a randomised comparison that resolves the contribution of surgery.
Overall, the findings support a coordinated assessment of systemic therapy and surgery. Treatment discussions should distinguish the review’s observed response patterns from the remaining uncertainty about comparative survival benefit.
Reference
Weil JBE et al. Chemotherapy and surgical outcomes for ovarian metastases from colorectal cancer: a narrative review. JAMA Oncol. Published online 24 September 2026. doi:10.1001/jamaoncol.2026.3634.