SUMMARY OF KEY RESEARCH FINDINGS
Tricuspid regurgitation (TR) is secondary in over 90% of cases, driven by chronic pressure or volume overload of the right heart.1 Pulmonary arterial hypertension (PAH)-related TR falls within the ventricular secondary phenotype, which carries the least favourable prognosis among secondary forms.2 In PAH, severe TR is an independent predictor of adverse outcome.3 Whether guideline-directed PAH therapy modifies TR severity has not been systematically examined.
The authors assessed this in two complementary scenarios: Group A comprised treatment-naïve patients initiated on upfront dual oral therapy with a phosphodiesterase type 5 (PDE5) inhibitor and an endothelin receptor antagonist; and Group B comprised patients on stable background therapy receiving add-on sotatercept.4
At baseline, 46% of Group A had moderate TR and 21% at least severe TR, while in Group B, 37.5% had moderate TR and 37.5% had severe TR. A significant reduction in TR severity was already apparent at first follow-up (median: 7.6 and 6.0 months, respectively) and persisted thereafter. At final follow-up (median: 3.0 and 2.5 years, respectively), TR was moderate or less in 80.6% (Group A) and 87.6% (Group B) of patients (Figure 1).
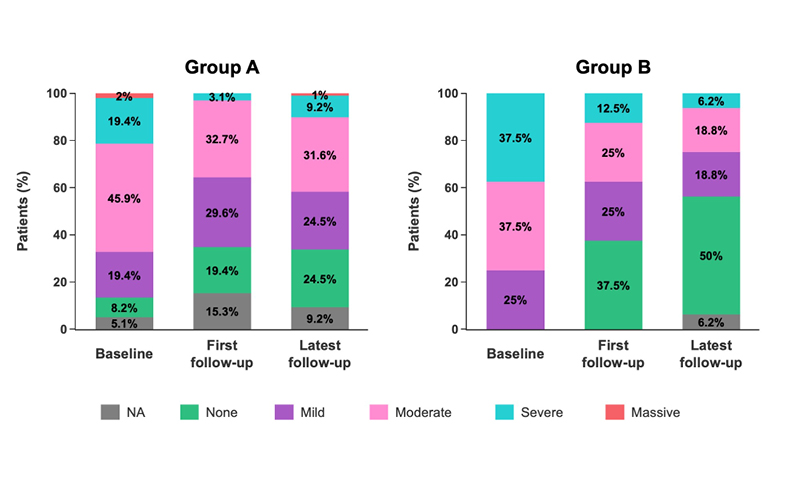
Figure 1: Evolution of TR severity under targeted PAH therapy in Group A and B.
NA: no interpretable echocardiogram available; PAH: pulmonary arterial hypertension; TR: tricuspid regurgitation.
These changes accompanied significant invasive improvements in mean pulmonary arterial pressure, pulmonary vascular resistance, and pulmonary artery compliance, alongside echocardiographic reductions in right atrial and right ventricular dimensions and improvements in right ventricular function and right ventricular–pulmonary artery coupling. Detailed results will be reported separately.
WHAT CHALLENGE DOES THIS ADDRESS?
In severe TR, current European Society of Cardiology (ESC)/European Association for Cardio-Thoracic Surgery (EACTS) guidelines define the therapeutic goal as a reduction of TR to moderate or less. Transcatheter therapy, however, is recommended only in the absence of severe right ventricular dysfunction or pre-capillary pulmonary hypertension; where either is present, optimal medical therapy is preferred. The guidelines list pulmonary vasodilators among the measures targeting the underlying cause, yet state that medical therapy has very limited effect on TR severity, a statement supported by a single trial that excluded patients with a systolic pulmonary artery pressure above 70 mmHg or fixed pre-capillary pulmonary hypertension.1,5 The authors’ cohort, with median baseline invasive systolic pulmonary artery pressure of 79.0 and 87.5 mmHg, falls largely outside that population. Here, regurgitation improved substantially on medical therapy alone, reaching the guideline-defined goal of moderate or less in 80.6% and 87.6% of patients.
RELEVANCE TO EUROPEAN CLINICAL PRACTICE
European guidelines recommend right heart catheterisation before any tricuspid intervention, due to the systematic underestimation of pulmonary pressures by echocardiography in severe TR.1 As the interventional repertoire for TR expands,6 with procedural volumes rising exponentially over the past decade,7 that requirement takes on added weight: the authors’ findings show that invasive assessment identifies patients in whom targeted PAH therapy alone may be sufficient to reduce TR severity.
WHAT ARE THE NEXT STEPS FOR THE RESEARCH?
What remains to be shown is whether the reduction in TR is driven by the haemodynamic improvement itself. Correlation analyses linking changes in invasive haemodynamics to changes in TR grade, vena contracta width, and tricuspid annulus diameter are required. A responder analysis identifying predictors of persistent high-grade TR despite haemodynamic improvement would be of particular clinical value, as this subgroup might be eligible for interventional therapy. Limitations include the single-centre, retrospective design without a control group, as well as the small study population in the sotatercept cohort. Validation requires prospective multicentre cohorts and follow-up powered for hard endpoints, in particular heart failure hospitalisation and all-cause mortality.