Abstract
Methaemoglobinaemia is a potentially life-threatening condition which is characterised by impaired oxygen delivery due to oxidation of haemoglobin. Methylene blue is the standard treatment; however, its availability may be limited and it is contraindicated in certain clinical situations. Ascorbic acid has been described as an alternative therapy, but evidence in adults, particularly with oral administration, is sparse. The authors describe a case series of four adult patients diagnosed with acquired methaemoglobinaemia who were treated with oral ascorbic acid. Clinical presentation, methaemoglobin levels, treatment regimen, time to response, and outcomes were analysed. All four patients presented with cyanosis and hypoxaemia unresponsive to supplemental oxygen. Methaemoglobin levels ranged from mild to moderate elevation. Oral ascorbic acid was administered as monotherapy, resulting in progressive clinical improvement and normalisation of methaemoglobin levels in all patients. None required methylene blue or additional rescue therapy. No adverse effects related to ascorbic acid were observed. This case series represents the largest reported adult cohort demonstrating successful treatment of methaemoglobinaemia using oral ascorbic acid alone. Oral vitamin C may be considered a safe, inexpensive, and effective therapeutic option in selected adult patients, especially when methylene blue is unavailable or contraindicated
Key Points
1. This article highlights methaemoglobinaemia as an important and often under-recognised cause of unexplained hypoxaemia that does not improve with supplemental oxygen and shows normal cardiopulmonary imaging. It emphasises the diagnostic value of co-oximetry and the need for clinical suspicion to avoid unnecessary investigations and inappropriate escalation of respiratory support.2. The manuscript describes a case series of four adult patients with mild to moderate methaemoglobinaemia, most consistent with congenital cytochrome b5 reductase deficiency, who were successfully treated with oral ascorbic acid alone. All patients showed gradual clinical improvement and reduction in methaemoglobin levels without the need for methylene blue or rescue therapy.
3. The key take-home message for clinicians is that oral ascorbic acid is a safe, inexpensive, and effective therapeutic option in selected adult patients with methaemoglobinaemia, particularly when methylene blue is unavailable or contraindicated. Early recognition and appropriate treatment can prevent misdiagnosis, prolonged hypoxaemia, and unnecessary interventions.
INTRODUCTION
Methaemoglobinaemia is a disorder of haemoglobin oxidation in which the iron moiety is converted from the ferrous to ferric state, rendering haemoglobin incapable of effective oxygen binding and delivery to tissues.1 Physiologically, methaemoglobin (MetHb) levels are maintained below 1% by endogenous enzymatic reduction systems, predominantly the NADH-dependent cytochrome b5 reductase pathway.2 Disruption of this balance results in accumulation of MetHb and functional anaemia, leading to hypoxaemia that is characteristically refractory to supplemental oxygen.3
Clinically, methaemoglobinaemia presents with cyanosis, fatigue, headache, dyspnoea, and chocolate-coloured arterial blood. Symptoms correlate imperfectly with MetHb levels and are influenced by comorbid cardiopulmonary disease and baseline oxygen reserve.4 A key diagnostic clue is the presence of a ‘saturation gap’, wherein pulse oximetry readings remain low despite relatively preserved arterial oxygen tension, necessitating confirmation by co-oximetry.5
Methaemoglobinaemia may be congenital or acquired. Congenital forms are rare and most commonly result from autosomal recessive deficiency of cytochrome b5 reductase (CYB5R3), leading to lifelong cyanosis of variable severity.6 Acquired methaemoglobinaemia is more frequently encountered and is associated with exposure to oxidising agents such as local anaesthetics, nitrates, dapsone, and certain antimicrobials.7
Intravenous methylene blue is considered the treatment of choice for symptomatic or moderate-to-severe methaemoglobinaemia; however, its use may be limited by availability, cost, or contraindications such as glucose-6-phosphate dehydrogenase deficiency.8 Ascorbic acid, a non-enzymatic reducing agent, has been reported as an alternative therapy, particularly in mild to moderate cases and resource-limited settings.9,10 Evidence supporting oral ascorbic acid use in adults remains limited, with most reports confined to isolated case reports.
The authors present a case series of four adult patients with methaemoglobinaemia successfully managed with oral ascorbic acid, highlighting diagnostic challenges and therapeutic considerations, and situating the findings within existing literature. To the authors’ knowledge, this case series represents the largest reported adult cohort evaluating oral ascorbic acid as monotherapy for methaemoglobinaemia, thereby expanding the existing evidence base and highlighting its potential role in selected clinical scenarios.
CASE SERIES: CASE DESCRIPTIONS
Patient 1
A 38-year-old male, office clerk by profession, presented to the Pulmonology outpatient department with a 3-day history of fever, cough, myalgia, and generalised fatigue.
There was no dyspnoea or chest pain, and he had no known comorbidities. On examination, vital parameters were stable except for an oxygen saturation (SpO₂) of 88% on room air. Chest auscultation was unremarkable, and chest radiograph was normal Figure 1.
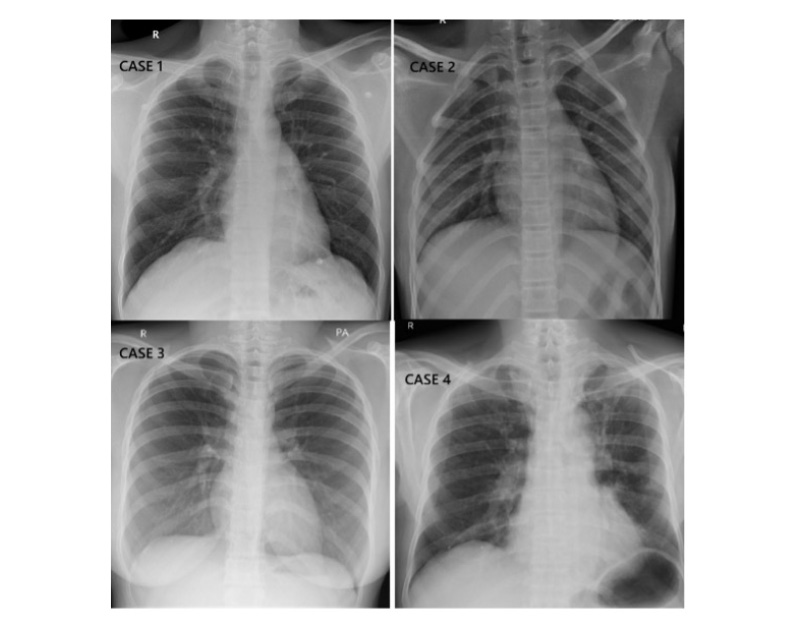
Figure 1: Chest X-rays of the patients.
In view of unexplained hypoxaemia, the patient was admitted for further evaluation. Routine laboratory investigations were within normal limits. Arterial blood gas (ABG) with co-oximetry analysis revealed methaemoglobinaemia with a MetHb level of 12.4% Table 1, and arterial blood appeared dark in colour Figure 2.
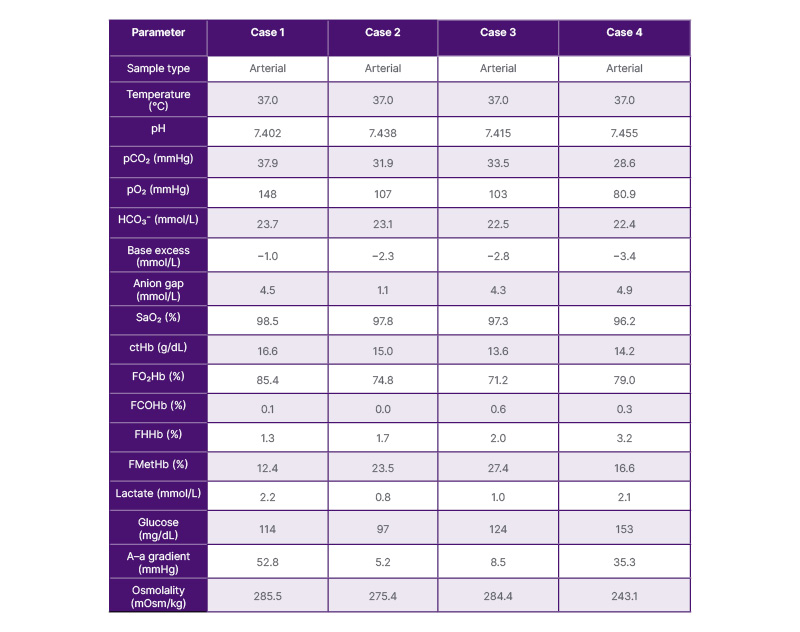
Table 1: ABG of the patients before starting the treatment.
A–a: alveolar–arterial; ABG: arterial blood gas; ctHb: concentration of total haemoglobin; FCOHb: fraction of carboxyhaemoglobin; FHHb: fraction of deoxyhaemoglobin; FMetHb: fraction of methaemoglobin; FO₂Hb: fraction of oxyhaemoglobin; HCO₃⁻: bicarbonate; pCO₂: partial pressure of carbon dioxide; pO₂: partial pressure of oxygen; SaO₂: arterial oxygen saturation.

Figure 2: Image showing dark-coloured blood.
Patient 2
A 19-year-old college-going female with a recent history of lower respiratory tract infection presented with persistently low SpO₂ readings. Clinical examination revealed stable vital signs except for an SpO₂ of 90% on room air. Chest auscultation and chest radiograph were normal Figure 1.
Routine haematological and biochemical investigations were within normal limits. ABG with co-oximetry analysis demonstrated methaemoglobinaemia with a MetHb level of 23.5% (Table 1), along with dark-coloured arterial blood.
Patient 3
A 23-year-old female accountant with no known comorbidities presented with cough, rhinitis, and headache of 3 days’ duration. She also reported a history of exertional dyspnoea and recurrent headaches over the preceding 3 years. On examination, vital signs were stable except for an SpO₂ of 83% on room air. Chest auscultation and chest radiograph were normal Figure 1. Routine blood investigations were within normal limits. ABG with co-oximetry analysis revealed methaemoglobinaemia with a MetHb level of 27.4% (Table 1), and arterial blood appeared dark.
Patient 4
A 75-year-old male with a history of previously treated ileocaecal tuberculosis, hypertension, and COPD presented with fever, productive cough, and dyspnoea of 5 days’ duration. On examination, pulse rate was 110 beats/min, blood pressure was 140/100 mmHg, and SpO₂ was 86% on room air. Chest auscultation revealed bilateral wheeze and crepitations. Chest radiograph showed bilateral increased bronchovascular markings Figure 1. Initial laboratory investigations were within normal limits. ABG analysis demonstrated Type 1 respiratory failure. The patient was treated with intravenous antibiotics, nebulisation, intravenous steroids, and supportive care, with clinical improvement. However, persistent hypoxaemia (SpO₂ ~90%) prompted further evaluation, and repeat ABG with co-oximetry analysis revealed methaemoglobinaemia with a MetHb level of 15.7%.
All patients were initiated on oral ascorbic acid therapy (vitamin C tablets 500 mg three times daily). Transfusion Medicine consultation was obtained in all cases for aetiological evaluation. NADH cytochrome b5 reductase assay demonstrated reduced enzyme activity in all patients, with values of 15.16, 25.08, 21.03, and 17.10 IU/g Hb in Patients 1–4, respectively. Two-dimensional echocardiograms were performed, revealing no structural or functional abnormalities. All patients showed gradual improvement in oxygen saturation with medical management alone. Follow-up ABG analysis demonstrated a significant reduction in MetHb levels (7.9%, 8.1%, 7.2%, and 6.2%, respectively). All patients were discharged in a haemodynamically stable condition on oral ascorbic acid and remain under outpatient follow-up.
DISCUSSION
This case series describes four adult patients with methaemoglobinaemia presenting with unexplained hypoxaemia and preserved cardiopulmonary imaging, emphasising the importance of early recognition and appropriate diagnostic evaluation. In all cases, low pulse oximetry readings persisted despite supplemental oxygen, a classic feature of methaemoglobinaemia attributable to altered light absorption characteristics of MetHb.3,5
All patients demonstrated reduced NADH cytochrome b5 reductase activity without identifiable oxidant exposure, consistent with congenital methaemoglobinaemia. Congenital CYB5R3 deficiency is a rare but under-recognised cause of chronic or intermittent cyanosis, often diagnosed late in adolescence or adulthood when hypoxaemia is incidentally detected.6,11 Type I deficiency, limited to erythrocytes, typically presents with isolated cyanosis and minimal systemic involvement, whereas Type II disease manifests with severe neurological impairment.6 The absence of neurological deficits in the authors’ patients supports a diagnosis of Type I congenital methaemoglobinaemia.
Prior studies have shown that infections, inflammatory states, and polypharmacy may act as precipitating factors even in the absence of classic exposures.7,12 Importantly, one patient with COPD exhibited persistent hypoxaemia despite clinical improvement of respiratory symptoms, illustrating how underlying lung disease can mask or exacerbate the clinical impact of relatively modest MetHb elevations.4
Methylene blue remains the standard antidote for symptomatic methaemoglobinaemia due to its rapid action via the NADPH-dependent pathway.8 However, its use may be restricted in certain populations, including patients with G6PD deficiency, renal failure, or limited access in resource-constrained settings.8,13 Additionally, methylene blue itself may paradoxically worsen haemolysis or methaemoglobinaemia if used inappropriately.13
Ascorbic acid has emerged as a viable alternative therapy due to its direct reducing properties and favourable safety profile. Several adult case reports and small series have demonstrated effective MetHb reduction using intravenous or oral ascorbic acid, particularly in mild to moderate cases.9,10,14 Oral administration, although slower in onset than methylene blue, offers advantages in terms of ease of administration, cost, and safety, especially for stable patients.14
Ascorbic acid has been reported as an effective alternative reducing agent in both congenital and acquired methaemoglobinaemia, with several adult case reports demonstrating gradual normalisation of methaemoglobin levels and improvement in oxygen saturation following oral administration, without the need for methylene blue.9,10,15
The gradual decline in MetHb levels observed in the authors’ patients aligns with previously published data indicating that ascorbic acid exerts a slower but sustained reducing effect compared to methylene blue.9,14 This characteristic makes it particularly suitable for non-life-threatening methaemoglobinaemia and for long-term management in congenital cases, where chronic suppression of MetHb formation is desirable.6,11
This series also underscores the diagnostic value of co-oximetry and enzyme assays in patients with unexplained hypoxaemia.
Failure to recognise methaemoglobinaemia may lead to unnecessary investigations and inappropriate escalation of respiratory support.5 Awareness of this condition among pulmonologists and internists is therefore essential.
CONCLUSION
In conclusion, methaemoglobinaemia should be suspected in patients with hypoxaemia disproportionate to clinical findings. Oral ascorbic acid represents a safe, effective, and accessible treatment alternative in mild to moderate cases and when methylene blue is contraindicated or unavailable. Larger prospective studies are warranted to define standardised dosing strategies and long-term outcomes.