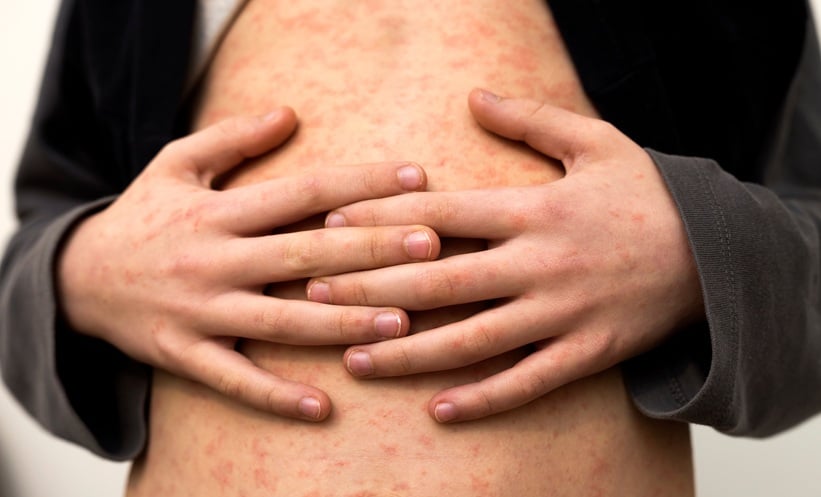
MEASLES outbreaks raise clinical concern over fatal neurological persistence driven by adaptive viral mutations in the human brain. As pediatric vaccination coverage declines and community transmission escalates across the United States, clinicians face an impending wave of delayed, devastating neuropathology. The primary threat centers on subacute sclerosing panencephalitis, a slow, progressive, and invariably lethal neurodegenerative disorder. While acute measles virus typically targets immune and respiratory epithelial cells through SLAMF1 and nectin-4 receptors, the central nervous system lacks these canonical entry proteins. Instead, measles virus enters neural parenchyma through trans-endocytosis from airway epithelia to olfactory neurons or via hematogenous spread across the blood-brain barrier.
Adaptive Mutations Drive Measles Neurovirulence
Once localized within brain tissue, measles virus overcomes the absence of classical receptors through remarkable collective genome evolution. Deep sequencing reveals that viral survival relies on collective infectious units, where complementary genome populations coreplicate within individual cells. Rather than existing as single virions, these assemblies accumulate coordinated alterations within the viral membrane fusion apparatus. Approximately seventy percent of clinical cases exhibit complete matrix protein inactivation, disrupting normal virion assembly while promoting deeper parenchymal penetration. Concurrently, universal alterations in the fusion protein cytoplasmic tail and ectodomain destabilization permit viral activation in cis by synaptic adhesion molecules, including CADM1 and CADM2. These hyperfusogenic properties facilitate direct, cell-to-cell viral transmission across synapses without generating cell-free virus.
Clinical Progression and Preventive Imperatives
The neurological trajectory of measles virus persistence follows four distinct clinical stages. Early manifestations present insidiously with cognitive decline and behavioral shifts, frequently progressing unnoticed for months. Stage II ushers in hallmark myoclonic jerks, seizures, and characteristic periodic complexes on electroencephalography, accompanied by diagnostic intrathecal measles antibody production. As widespread cortical degradation ensues in stages III and IV, patients deteriorate into spasticity, coma, and vegetative states. Surviving two years post-diagnosis remains below fifty percent. With antiviral agents and immunomodulators proving largely ineffective against established collective units, universal measles vaccination stands as the only validated defense to prevent fatal central nervous system infection.
Reference
Cattaneo R et al. Subacute Sclerosing Panencephalitis: How Measles Virus Adapts to the Brain. Annu Rev Virol. 2026;13:7.1-7.23.
Featured Image: bilanol on Adobe Stock.