Abstract
Background: Complex coronary artery disease presents a severe therapeutic challenge when coexisting with advanced age and active malignancy. Patients with active cancer are frequently deemed ineligible for surgical revascularisation due to frailty, bleeding risks, and cancer-related coagulopathies, despite complete revascularisation being a key determinant for long-term survival. The authors report a case where mechanical circulatory support enabled complete percutaneous revascularisation in an octogenarian patient with active prostate cancer under oncologic therapy who was previously turned down for surgery.
Case Summary: An 81-year-old male with active, hormone-responsive prostate cancer (Eastern Cooperative Oncology Group [ECOG] Performance Status: 1; Activities of Daily Living [ADL]: 6/6) presented with non-ST-segment elevation acute coronary syndrome. Coronary angiography revealed extreme anatomical complexity (SYNTAX Score: 48; British Cardiovascular Intervention Society-1 Myocardial Jeopardy Score (BCIS-JS): 12/12), including a calcified distal left main bifurcation lesion, severe multivessel disease, and a functional chronic total occlusion of the circumflex artery. Following multidisciplinary heart-oncology team evaluation, coronary artery bypass grafting was not recommended due to high procedural risks associated with the patient’s frailty, increased bleeding risks, and the imperative to avoid delay in oncology treatment. Prophylactic insertion of an Impella CP® (Abiomed, Danvers, Massachusetts, USA) microaxial flow pump provided active haemodynamic support during high-risk percutaneous coronary intervention. Complex stenting and intravascular ultrasound-guided optimisation were successfully executed. Despite a high iodinated contrast load (380 mL), remarkable renal functional preservation was observed (creatinine: 1.10 mg/dL baseline to 1.20 mg/dL post-percutaneous coronary intervention, normalising to 0.90 mg/dL at follow-up).
Discussion: This case illustrates the feasibility and safety of protected percutaneous coronary intervention in cardio-oncology. Microaxial flow pumps maintain renal and systemic perfusion during high ischaemia risk procedures, offering an effective, organ-protective alternative to surgery in complex, frail cancer populations.
Key Points
1. Patients with active malignancy undergoing high-risk PCI have increased haemodynamic, ischaemic, and bleeding risks, making patient selection and individualised mechanical circulatory support strategies particularly important in this complex population.2. This review discusses the use of Impella CP® during high-risk PCI in patients with cancer, including patient selection, haemodynamic considerations, vascular access, procedural challenges, complications, and reported clinical outcomes.
3. Careful pre-procedural planning, multidisciplinary cardio-oncology evaluation, and appropriate periprocedural management may reduce vascular and bleeding complications and facilitate safe revascularisation in selected patients with cancer undergoing high-risk PCI.
INTRODUCTION
Complex coronary artery disease (CAD), characterised by extensive anatomical complexity and severe atherosclerotic burden, presents a growing therapeutic challenge when coexisting with advanced age and active malignancy.1,2 This patient cohort, encompassed under the concept of Complex Higher-Risk (and Indicated) Patients (CHIP), has historically been excluded from randomised clinical trials and deemed ineligible for coronary artery bypass grafting due to prohibitive surgical risk, often leaving them transitioned to palliative medical therapy with poor prognosis.3,4
Managing complex CAD in octogenarians with concurrent active cancer introduces significant clinical dilemmas.1,2 Age-related vascular fragility, chronic systemic inflammation, and cancer-treatment-induced coagulopathies markedly elevate both ischaemic and haemorrhagic risks during percutaneous interventions.5 Active oncological diagnoses add unique management layers; bone marrow suppression, malignancy-associated hypercoagulability, and the requirement for uninterrupted oncology treatments limit traditional invasive options.6 However, when an active cancer carries a favourable long-term prognosis (e.g., non-metastatic, hormone-responsive prostate cancer), withholding revascularisation based solely on oncologic history or age may lead to preventable cardiovascular mortality.7 Recent evidence confirms that complete revascularisation remains a primary determinant for survival in complex CAD.8
In this cardio-oncology context of high-risk CAD combined with active oncologic therapy, percutaneous mechanical circulatory support has shifted the intervention paradigm from ‘rescue’ to ‘prophylactic protection’.9 Microaxial flow devices, such as the Impella CP® (Abiomed, Danvers, Massachusetts, USA), preserve systemic, coronary, and organ perfusion during iatrogenic ischaemia induced by complex inflation cycles, rendering extensive revascularisation haemodynamically tolerable.8,10 Herein, the authors present the case of an octogenarian patient with active prostate cancer under combined androgen deprivation therapy and radiotherapy who successfully underwent intravascular ultrasound-guided, Impella CP-supported complete revascularisation.
CASE PRESENTATION
Baseline Patient Profile and Cardio-oncologic Stratification
An 81-year-old male presented to the emergency department with a 24-hour history of New York Heart Association (NYHA) functional Class III and Canadian Cardiovascular Society (CCS) Class IV unstable angina, secondary to a non-ST-segment elevation acute coronary syndrome.11 His baseline functional status was excellent, with an Eastern Cooperative Oncology Group (ECOG) performance status of 1 and complete independence in activities of daily living (Barthel Index: 100/100; Activities of Daily Living [ADL]: 6/6). His oncologic history was notable for intermediate-risk, non-metastatic adenocarcinoma of the prostate (cT2aN0M0, Gleason score 3+4=7), diagnosed 2 years prior. He was actively receiving monthly luteinising hormone-releasing hormone agonist therapy (goserelin) and ongoing localised external beam radiation therapy. At admission, his prostate-specific antigen was well-controlled (4.8 ng/mL) without evidence of clinical or biochemical progression.
The admission cardiovascular risk profile was severe: a Thrombolysis in Myocardial Infarction (TIMI) Risk Score of 5 and Global Registry of Acute Coronary Events (GRACE) Risk Score of 231, estimating an in-hospital mortality >21%.11 The 12-lead ECG demonstrated a high-risk ischaemic pattern characterised by ST-segment elevation in the augmented voltage right lead, with concomitant widespread ST-segment depression across multiple leads.11 (Figure 1) Transthoracic echocardiography revealed a left ventricular ejection fraction (LVEF) of 41% with anterior-apical hypokinesis, preserved right ventricular function (tricuspid annular plane systolic excursion 21 mm, S’ wave 9.2 cm/s), mild degenerative aortic valve sclerosis without stenosis (mean gradient 6 mmHg), and absence of significant mitral or tricuspid valve pathologies.
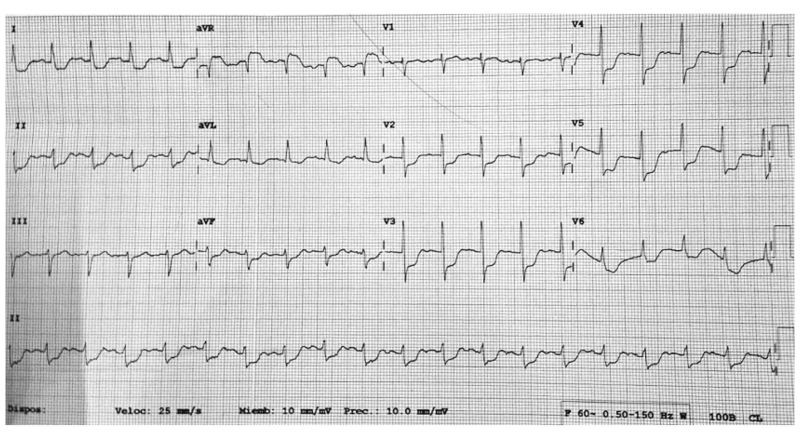
Figure 1: Admission ECG.
High-risk pattern showing ST-segment elevation in lead aVR with diffuse ST-segment depression in >7 leads. aVR: augmented vector/voltage right.
Laboratory Investigations
Serial laboratory evaluations throughout the hospital stay and outpatient follow-up are summarised in Table 1. Baseline haemoglobin was 13.0 g/dL with a platelet count of 293×103/mcL and normal coagulation parameters (prothrombin time: 11.8 seconds; international normalised ratio: 1.03; activated partial thromboplastin time: 49.0 seconds). Serum creatinine was 1.10 mg/dL; estimated glomerular filtration rate 64 mL/min/1.73m2 with elevated urea (64.0 mg/dL). Cardiac biomarkers confirmed myocardial injury with elevated CK-MB (30.0 U/L).
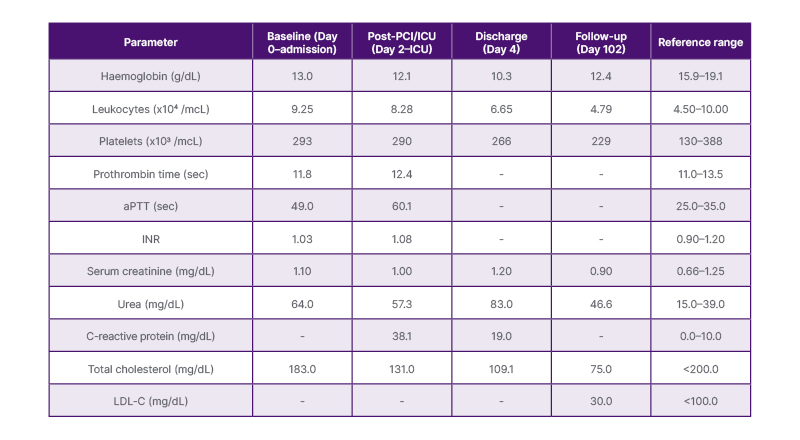
Table 1: Serial laboratory findings throughout hospitalisation and follow-up.
aPTT: activated partial thromboplastin time; INR: international normalised ratio; LDL-C: low-density lipoprotein cholesterol; PCI: percutaneous coronary intervention.
Coronary Angiography Results and Multidisciplinary Heart-Oncology Team Decision
Diagnostic coronary angiography (Figure 2)via right radial access revealed extreme anatomical complexity (SYNTAX Score: 48):12
- Left main (LM): severe calcification with 95% concentric distal bifurcation stenosis
- Left anterior descending (LAD): diffuse, heavily calcified disease involving a long bifurcation lesion (Medina 1-1-1) with the first diagonal branch (70–95%), displaying TIMI 2 antegrade flow
- Circumflex: functional chronic total occlusion (CTO) in the distal segment, TIMI 0 flow, supported by Rentrop 3 collateral vessels
- Right coronary artery: severe diffuse distal disease (95%) with TIMI 3 flow
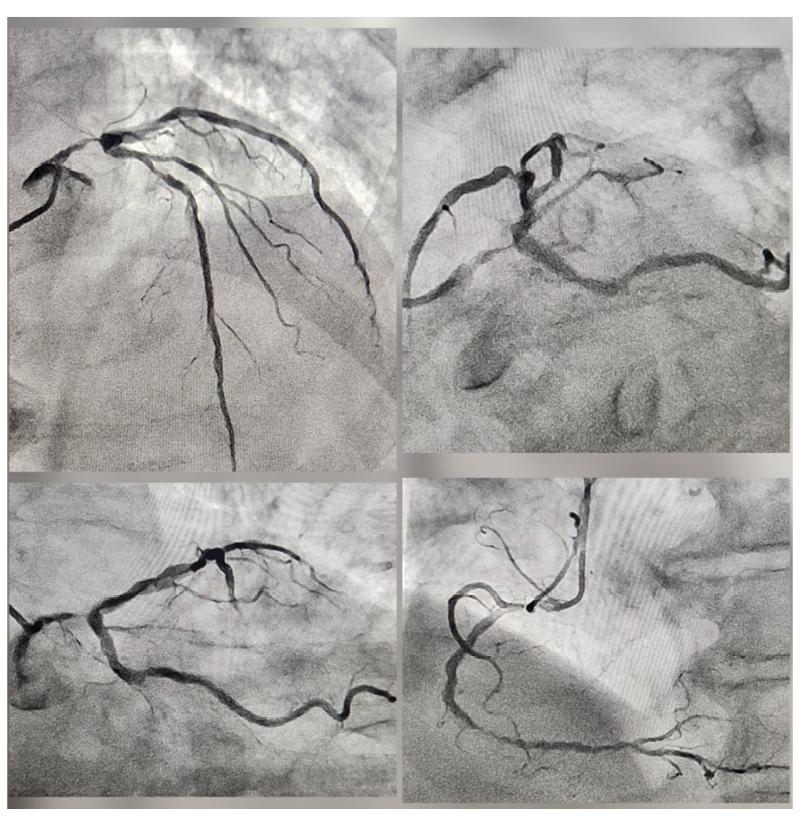
Figure 2: Baseline coronary angiography.
Composite projections illustrating extreme anatomical complexity (SYNTAX score 48), featuring critical calcified distal left main/LAD disease, circumflex occlusion, and severe RCA stenosis.
LAD: left anterior descending; RCA: right coronary artery.
The case was analysed by a multidisciplinary heart team, composed of Interventional Cardiology, Cardiac Surgery, an echocardiography service, intensive cardiovascular therapy, and Urologic Oncology. Although standard surgical calculators yielded moderate mortality estimates (Society of Thoracic Surgeons (STS) score 3.3%, European System for Cardiac Operative Risk Evaluation II [EuroSCORE ii] 4.35%),3,4 coronary artery bypass grafting was not recommended due to high procedural risks associated with patient’s frailty, increased bleeding risks, and the imperative to avoiding delay in oncology treatment.6 A British Cardiovascular Intervention Society-1 Myocardial Jeopardy Score (BCIS-JS ) of 12/12 and a UK CHIP-percutaneous coronary intervention (PCI) Score of 11 predicted a 14.4% in-hospital major adverse cardiovascular events risk, justifying prophylactic mechanical circulatory support for PCI.12,13
Protected PCI Procedure
Under local anaesthesia, real-time ultrasound guidance was used to perform a micropuncture of the left common femoral artery above the bifurcation, following fluoroscopic exclusion of prohibitive anterior wall calcification.12 Two suture-mediated closure devices (Perclose™ ProStyle™ [Abbott, Abbott Park, Illinois, USA]) were pre-deployed, and a 14 French (Fr) arterial sheath was positioned. An Impella CP microaxial flow pump was successfully placed across the aortic valve, establishing active haemodynamic support at performance level P-4 (3.2 L/min).9 Secondary 6 Fr right radial access was utilised for coronary engagement.
- Circumflex CTO intervention: Crossing the calcified CTO required a guide extension catheter (Guidezilla) and an inch-worming technique. A XIENCE Sierra® (Abbott) 2.0 times 23 mm drug-eluting stent (DES) was deployed and post-dilated to 2.24 mm.
- LM and LAD intervention: Lesion preparation of the calcified distal LM/LAD was accomplished with semi-compliant balloons. Intravascular ultrasound confirmed severe circumferential calcification (>260º arc; length >5 mm), prompting aggressive preparation. A Synergy 2.75×32 mm DES (Boston Scientific, Marlborough, Massachusetts, USA) was deployed in the mid-proximal LAD, followed by a provisional XIENCE Sierra (Abbott) 3.5×38 mm DES extending from the LAD into the LM ostium. Optimisation was performed using the proximal optimisation technique with a 4.0 mm non-compliant balloon, achieving an adequate final minimal luminal area (8.2 mm2 in LM; 6.1 mm2 in LAD).
- Right coronary artery intervention: Revascularisation was completed with two overlapping Synergy DES (Boston Scientific; 3.0×20 mm and 3.5×20 mm) in the proximal and distal segments, post-dilated to 3.22 mm and 3.87 mm.
Final angiography (Figure 3) demonstrated TIMI 3 flow in all vessels with zero residual stenosis. Throughout repeated balloon inflations and transient myocardial ischaemia, the Impella CP maintained continuous systemic cardiac output without episodes of hypotension or ventricular arrhythmias.9 The device was explanted in the catheterisation laboratory, achieving complete vascular haemostasis via the pre-deployed ProStyle sutures without local complications. The total procedure time was 110 minutes, with 380 mL of iodinated contrast administered.
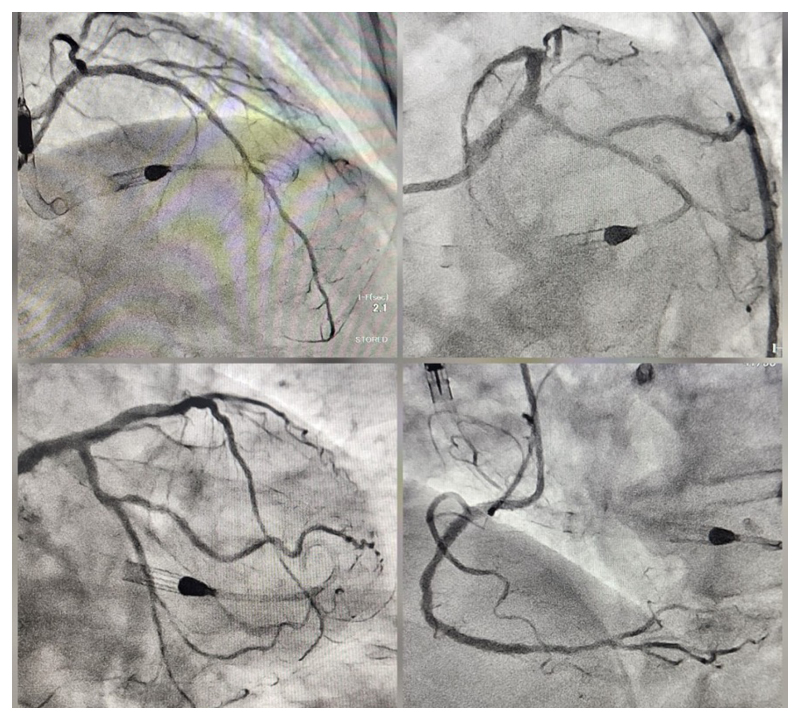
Figure 3: Protected PCI and final angiographic result.
Fluoroscopic view of Impella CP® in proper position across the aortic valve during complex stenting, and final angiogram confirming TIMI 3 flow in all epicardial vessels.
Impella CP®: Abiomed, Danvers, Massachusetts, USA; PCI: percutaneous coronary intervention; TIMI: thrombolysis in myocardial infarction.
Postoperative Course and Follow-up
The patient was transferred to the Coronary Care Unit. Continuous intraoperative and post-procedural urine output was maintained at >1.3 mL/kg/h (2,450 mL total over 24 hours) without high-dose loop diuretics.14 Despite the high contrast load, acute kidney injury did not develop; serum creatinine at 24 hours post-PCI was 1.00 mg/dL (1.20 mg/dL at Day 4 discharge), reflecting preserved renal clearance.14
Haemoglobin decreased from 13.0 g/dL to a nadir of 10.3 g/dL at discharge without overt vascular access or gastrointestinal bleeding, consistent with haemodilution and minor access oozing. The patient was discharged on Day 4 on dual antiplatelet therapy (DAPT) with aspirin 100 mg per day and clopidogrel 75 mg per day (planned for a shortened 3-to-6-month duration given oncology bleeding trade-offs), atorvastatin 40 mg per day, bisoprolol 2.5 mg per day, sacubitril with valsartan 24/26 mg twice daily, and ongoing goserelin.7 At the 3-month follow-up, the patient was in NYHA Class I/CCS functional Class 0 with stable haemoglobin (12.4 g/dL), excellent lipid control (low-density lipoprotein cholesterol 30 mg/dL), and preserved renal function (creatinine 0.90 mg/dL).
DISCUSSION
Anatomical Complexity and Mechanical Support Rationale
A Syntax Score of 48 places this patient in the extreme tail of anatomical risk, well above the mean scores reported in pivotal trials such as PROTECT II (29±13) and PROTECT III (34±11).8,10 In unprotected left main bifurcation interventions, transient balloon occlusions induce acute, obligatory ischaemia across >75% of the myocardium.13 In patients with impaired baseline LVEF, this ischaemic stress triggers severe left ventricular end-diastolic pressure spikes, myocardial stunning, and irreversible circulatory collapse.9,13 Unlike the intra-aortic balloon pump, which depends on native synchronised ventricular contraction, the microaxial flow pump provides non-pulsatile, active cardiac unloading (3.0–3.5 L/min), lowering left ventricular end-diastolic pressure, suppressing wall stress, and preserving systemic mean arterial pressure independently of native rhythm during complex bifurcations.8,9 Furthermore, as observed in the USpella registry, extensive support-assisted revascularisation in low-to-borderline LVEF directly correlates with functional recovery and major adverse cardiovascular event reduction.15
Cardio-oncology Balance: Bleeding versus Thrombosis
Managing complex CAD in patients with active malignancy requires navigating a heightened prothrombotic state (paraneoplastic tissue factor expression, endothelial dysfunction) alongside an elevated bleeding risk driven by pelvic radiotherapy and potential bone marrow suppression.6,7 DAPT selection requires precision.2 While potent P2Y12 inhibitors (prasugrel, ticagrelor) carry excess bleeding hazards in cancer, clopidogrel combined with modern thin-strut DES offers an optimal safety-efficacy profile.6,7 Contemporary DES exhibit rapid endothelialisation, permitting shortened DAPT regimens (3–6 months) if urgent oncologic procedures or bleeding events occur.7
Large-Bore Access in Calcified Vasculature
Inserting a 14 Fr sheath through calcified femoral arteries in octogenarians poses significant risks of vessel rupture, dissection, or closure failure.12 Meticulous anterior-wall micropuncture under real-time ultrasound guidance, combined with pre-closing suture techniques (Perclose ProStyle), is essential to avoid calcified plaques that could tear fragile vessel walls upon suture tightening.
Active Haemodynamic Renal Protection
A key observation in this case was the complete preservation of renal function despite a 380 mL contrast volume.14 Contrast-induced acute kidney injury stems from renal medullary hypoxia and direct tubular toxicity, exacerbated by intra-procedural hypotension.14 Impella support maintains continuous renal perfusion pressure and suppresses reflex neurohormonal vasoconstriction during transient hypotension, acting as an active haemodynamic buffer against renal ischaemia during high-contrast interventions.14
CONCLUSION
Prophylactic Impella CP support enables safe and complete percutaneous revascularisation in octogenarians presenting with extreme anatomical complexity (Syntax Score >40) who are not recommended for surgical revascularisation due to high procedural risks associated with patient frailty, elevated bleeding hazards, and the imperative to prevent oncology treatment delays. Furthermore, active mechanical haemodynamic support preserves continuous renal perfusion pressure during high-contrast complex interventions, effectively mitigating the risk of contrast-induced acute kidney injury. Ultimately, structured multidisciplinary collaboration within a dedicated heart-oncology team remains paramount to successfully navigate and balance competing ischaemic, haemorrhagic, and oncological priorities in high-risk patients.