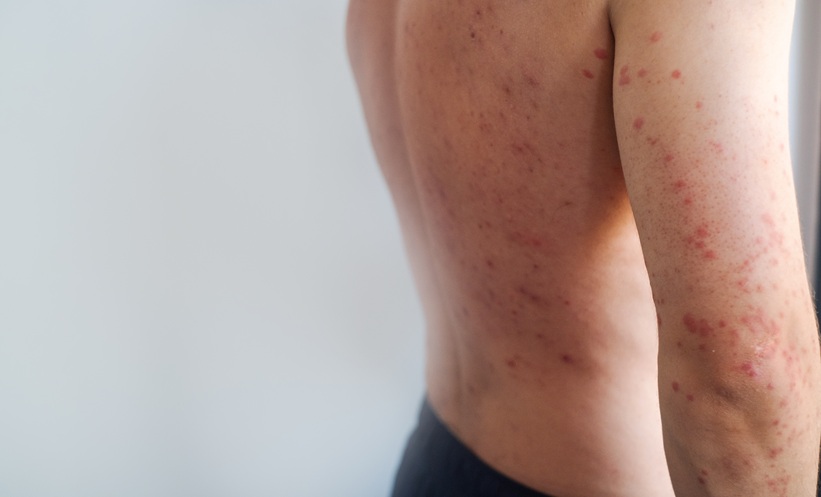
MEASLES diagnostic delays affect nearly seven percent of patients, increasing exposure risks across outpatient healthcare settings. A retrospective case-crossover investigation evaluating 4,651 measles cases across two decades of longitudinal United States health insurance claims revealed that 6.9 percent of infected individuals experienced at least one missed diagnostic opportunity during the two weeks preceding their index diagnosis. For patients who encountered delayed recognition, the mean duration of measles diagnostic delays before clinical confirmation was 4.05 days. Furthermore, an estimated 1.7 percent of patients experienced diagnostic delays extending a full week or longer.
Setting Distribution and Missed Opportunities
The overwhelming majority of missed opportunities occurred in ambulatory care environments. Outpatient clinics accounted for 81.0 percent of missed diagnostic encounters, whereas emergency departments represented 14.4 percent, inpatient facilities represented 3.9 percent, and observational units comprised 0.7 percent. Because the measles virus spreads efficiently through fine aerosolized particles that remain suspended in air currents for hours, diagnostic lags in ambulatory centers generate acute transmission risks. In community clinics and waiting rooms lacking negative pressure isolation suites, delayed recognition directly compromises routine outpatient infection control and exposes vulnerable contacts.
Clinical Predictors and Prescribing Patterns
Multivariable regression models identified key demographic and management factors that significantly heightened the likelihood of measles diagnostic delays. Patients younger than two years of age demonstrated the greatest risk for delayed diagnosis compared to older pediatric cohorts and adults. Infants and toddlers cannot verbalize prodromal symptoms, and clinicians often mistake early viral exanthems for benign childhood rashes. In addition, the receipt of respiratory antibiotics during the two-week diagnostic window was associated with a greater than sixfold increase in the odds of delay. When clinicians misdiagnose prodromal measles as common bacterial otitis or bronchitis, empiric antibiotic prescriptions can provide false reassurance, leading caregivers to postpone re-evaluation until systemic rash appears. In the face of expanding outbreaks and declining immunization rates, physicians must maintain an elevated index of clinical suspicion for early measles presentations to intercept hospital and community transmission.
Reference
Arakkal AT et al. Estimating the incidence and duration of diagnostic delays for measles. Infect Control Hosp Epidemiol. 2026;doi:10.1017/ice.2025.10393.