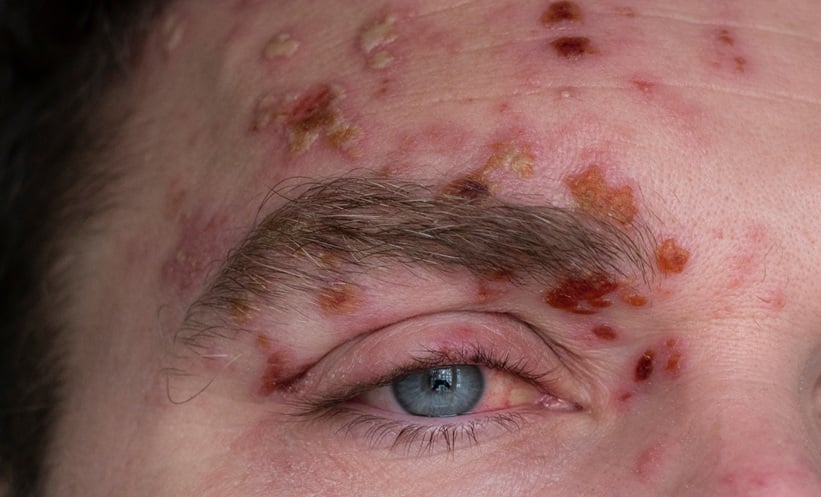
PROMPT initiation of intravenous acyclovir therapy significantly curbs lasting deficits in adult varicella zoster virus meningitis. A ten-year clinical investigation revealed that varicella zoster virus represents the most common identifiable cause of aseptic meningitis, accounting for more than one-third of adult admissions. Despite standard care protocols, over forty-three percent of affected individuals experienced residual neurological symptoms at hospital discharge. This rate substantially exceeded the thirteen percent observed in patients with other forms of aseptic meningitis.
Multivariate regression demonstrated that treatment timing serves as a decisive modifiable prognostic factor. Every single day of delay before starting intravenous acyclovir increased the odds of residual neurological symptoms at discharge by thirty point three percent. Baseline functional status also independently influenced recovery, with higher pre-onset disability scores predicting poorer outcomes. Notably, preceding outpatient treatment with oral antiviral agents failed to prevent functional decline or improve recovery metrics. More than forty percent of patients who developed central nervous system involvement had received prior oral therapy for cutaneous herpes zoster, yet their rates of residual disability matched those treated directly with intravenous infusions. This failure highlights the insufficient cerebrospinal fluid penetration of standard oral regimens once central invasion occurs.
Atypical Presentations and Diagnostic Pitfalls
Clinical presentations differed markedly by patient age, introducing substantial diagnostic complexity. Patients aged fifty and older frequently lacked classical meningeal signs, showing significantly lower rates of headache and neck stiffness compared to younger adults. In addition, cerebrospinal fluid analysis in older patients demonstrated attenuated pleocytosis, reflecting age-related immunosenescence. Although older adults experienced longer hospitalizations and greater peak disability during admission, their rates of discharge deficits were comparable to younger cohorts once intravenous antiviral therapy was completed.
Because classic physical findings and marked inflammatory markers are frequently blunted in older individuals with varicella zoster virus meningitis, clinicians cannot rely on typical presentations to rule out central pathology. Immediate lumbar puncture and empiric intravenous acyclovir must be initiated upon the earliest clinical suspicion rather than waiting for confirmatory viral assays.
Reference
Tasaki K et al. Prognostic Factors and Clinical Characteristics of Varicella Zoster Virus Meningitis: Impact of Treatment Delay and Age-Related Differences in a Japanese Tertiary Hospital. Neurol Int. 2026;18(7):130.