Abstract
Introduction: Paraneoplastic cerebellar degeneration (PCD) is a rare immune-mediated neurological syndrome associated with Hodgkin lymphoma (HL). It typically presents with subacute cerebellar dysfunction and is strongly linked to anti-Tr/delta/notch-like epidermal growth factor-related receptor (DNER) antibodies directed against cerebellar Purkinje cells.
Objective: To describe a case of HL presenting with PCD and anti-Tr/DNER antibodies, highlighting the clinical, radiological, and immunological features, and to contextualise the findings within the existing literature.
Case report: This article reports the case of a woman in her early 50s who presented with rapidly progressive cerebellar syndrome characterised by gait ataxia, severe dysarthria, and cerebellar signs. Cerebrospinal fluid analysis showed mononuclear pleocytosis with normal protein and glucose levels. Brain MRI demonstrated subtle bilateral cerebellar cortical hyperintensities. Anti-Tr/DNER antibodies were detected in serum and cerebrospinal fluid. Subsequent imaging revealed widespread lymphadenopathy, and lymph node biopsy confirmed classical HL (Ann Arbor Stage IIA). The patient received four cycles of ABVD (doxorubicin, bleomycin, vinblastine, and dacarbazine) chemotherapy alongside immunomodulatory treatment for PCD, including corticosteroids, plasmapheresis, and rituximab.
Results: Complete oncological remission was achieved; however, anti-Tr antibodies persisted and no significant neurological recovery occurred, with ongoing ataxia, dysarthria, and oculo-vestibular symptoms.
Conclusion: This case underscores the role of anti-Tr/DNER-associated PCD as an early indicator of HL and highlights the striking dissociation between excellent oncological outcomes and poor neurological prognosis. Early recognition and prompt treatment are essential, as irreversible cerebellar damage may occur despite successful tumour control.
Key points
1. Anti-Tr/delta/notch-like epidermal growth factor-related receptor-associated paraneoplastic cerebellar degeneration often precedes Hodgkin lymphoma diagnosis, frequently leading to detection at an early stage.2. Although oncological prognosis is generally favourable, neurological improvement remains limited in the majority of reported patients.
3. Anti-Tr/delta/notch-like epidermal growth factor-related receptor antibody titre fluctuations do not reliably parallel neurological clinical evolution.
INTRODUCTION
Paraneoplastic cerebellar degeneration (PCD) is a rare neurological syndrome that is frequently associated with underlying malignancies, such as Hodgkin lymphoma (HL). It is characterised by a subacute cerebellar dysfunction, immunologically mediated by anti-Tr/delta/notch-like epidermal growth factor-related receptor (DNER) antibodies directed against Purkinje cells.1
Objective
To present a clinical case of HL with neurological onset in the form of PCD and positive anti-Tr/DNER antibodies, outlining the clinical, radiological, and immunological course, and comparing it with data reported in the literature. This case is notable for the presence of early cerebellar cortical hyperintensity on MRI, persistence of anti-Tr antibodies despite complete oncological remission, and the presence of atypical extracerebellar neurological manifestations.
CASE DESCRIPTION
This report describes the case of a female patient in her early 50s who was admitted with a subacute neurological syndrome characterised by gait instability, severe dysarthria, and cerebellar signs. Cerebrospinal fluid analysis revealed mononuclear pleocytosis (150 cells), with normal protein and glucose levels. Brain MRI, fluid-attenuated inversion recovery, and T2 sequences (Figure 1) showed bilateral cerebellar cortical hyperintensity without diffusion restriction or contrast enhancement, and there was no evidence of cerebellar atrophy at presentation. Anti-Tr (DNER) antibodies were identified in both serum and cerebrospinal fluid. A thoracoabdominopelvic CT scan revealed lymphadenopathy in the axillary, retropectoral, supraclavicular, and mediastinal regions. Lymph node biopsy confirmed a diagnosis of classical HL. Alternative causes of cerebellar syndrome were excluded, including infectious, metabolic, toxic, and structural aetiologies. PET/CT staging could not be performed due to progressive neurological deterioration (anarthria, bradyphrenia, heteroaggression); however, based on the CT findings, the disease was consistent with Ann Arbor Stage IIA. Treatment for PCD was initiated early with corticosteroid pulses and five sessions of plasmapheresis due to rapid neurological deterioration. Rituximab was subsequently administered. Following confirmation of HL, the patient received four cycles of ABVD (doxorubicin, bleomycin, vinblastine, and dacarbazine) chemotherapy.
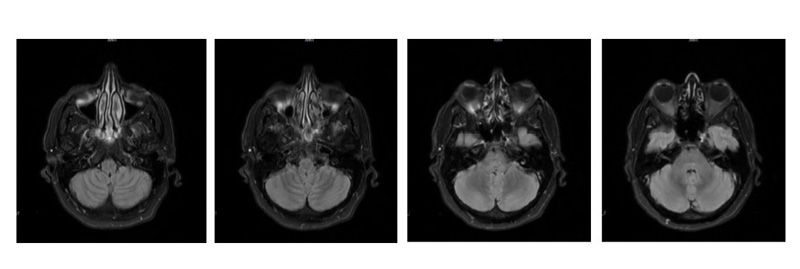
Figure 1: Diffusion-weighted brain MRI showing bilateral cerebellar cortical hyperintensity.
Axial brain MRI slices on diffusion-weighted imaging show a questionable subtle cortical signal hyperintensity in both cerebellar hemispheres, diffusely distributed, without a clear decrease in apparent diffusion coefficient values, which may suggest mild cortical oedema, probably related to paraneoplastic cerebellar degeneration.
RESULTS
Following ABVD, complete remission was achieved on CT. However, anti-Tr antibodies remained positive, and no significant neurological improvement was observed, with persistent symptoms of nausea, dizziness, dysarthria, bradylalia, and ataxia (Figure 2).
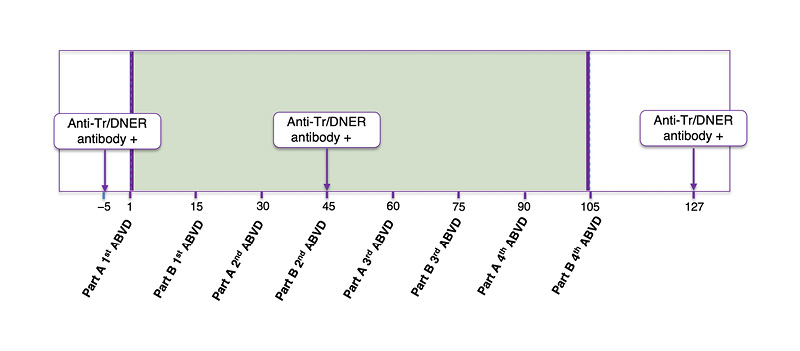
Figure 2: Timeline of treatment and serum anti-Tr/DNER antibody titre measurements.
ABVD: doxorubicin, bleomycin, vinblastine, and dacarbazine; DNER: delta/notch-like epidermal growth factor-related receptor.
DISCUSSION
PCD has been described in gynaecological cancers such as ovarian and breast cancer, as well as in small-cell lung cancer and HL.2 The presence of anti-Tr/DNER antibodies is strongly associated with HL.3 Rare associations with other tumours have been reported, including Warthin tumour,4 as well as limbic encephalitis with anaplastic large cell lymphoma.5 Pathophysiologically, the condition involves the loss of Purkinje cells in the cerebellum, resulting in subacute cerebellar dysfunction. The target antigen of these antibodies is DNER, a transmembrane protein expressed in Purkinje cells dendrites.1
As summarised in (Table 1), previously published cases of anti-Tr/DNER-associated PCD indicate that this condition may act as an early warning signal within the body. As noted by Campana and Silva1 in their systematic review, HL is typically detected at an early stage (I or II) in three out of four cases associated with these antibodies. This observation is consistent with the case series by Bernal et al.,3 in which 76% of patients had localised-stage disease at the time of diagnosis. From a pathophysiological perspective, Campana and Silva1 suggest that the paraneoplastic syndrome may be linked to an enhanced immune response against tumour cells, facilitating early detection before the cancer has disseminated. In this context, the onset of ataxia allows the identification of a neoplasm that would otherwise remain occult. According to the reviewed literature, ataxia precedes the diagnosis of HL in approximately 80% of cases. For the patient described in this article, the onset of the neurological condition and subsequent detection of anti-Tr antibodies were the key factors that prompted oncological screening, which revealed localised-stage HL.
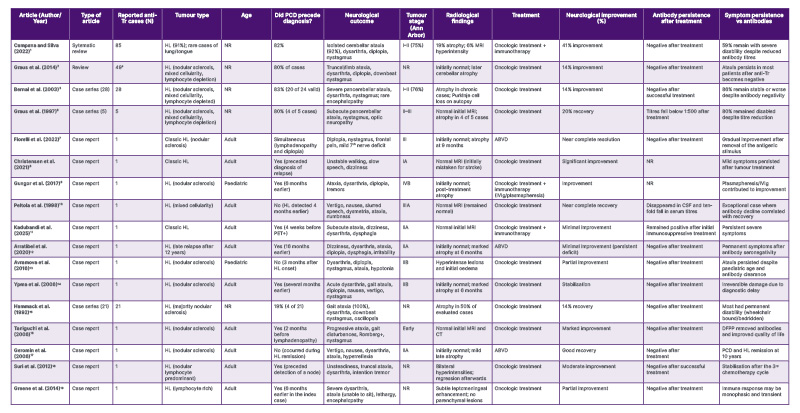
Table 1: Summary of published reports on anti-Tr/DNER PCD associated with HL reviewed in the literature.1-3,6-19
aGraus2 integrates data from the Bernal et al.3 and Hammack et al.15 series.
ABVD: doxorubicin, bleomycin, vinblastine, and dacarbazine; CSF: cerebrospinal fluid; DFPP: double filtration plasmapheresis; DNER: delta/notch-like epidermal growth factor-related receptor; HL: Hodgkin lymphoma; IVIg: intravenous Ig; PCD: paraneoplastic cerebellar degeneration; NR: not reported; vs: versus.
A marked disparity exists in the reviewed literature between the success of oncological treatment and functional recovery. According to the systematic review by Campana and Silva,1 which analysed 85 cases of patients with anti-Tr/DNER antibodies detected in serum or plasma (of whom over 90% had an underlying tumour), while the oncological response was excellent (with complete responses approaching 90% among treated cases), the neurological prognosis remained poor. Although their review reports improvement in 41% of cases, larger historical series analysed by Bernal et al.3 and Graus et al.6 agree that the rate of recovery or significant improvement is only around 14%. However, there are case reports, such as those by Fiorelli et al.,7 Christensen et al.,8 Gungor et al.,9 and Peltola et al.,10 in which the neurological course following treatment of the underlying HL was associated with improvement, or even resolution, of neurological symptoms. In contrast, in published cases, such as the recent report by Kadubandi et al.,11 as well as those by Arratibel et al.,12 Avramova et al.,13 Ypma et al.,14 and the series by Graus et al.,2 Bernal et al.,3 and Hammack et al.,15 neurological symptoms have been reported to persist without improvement or to become established despite remission of the underlying HL.
Regarding radiological findings, in this case the cortical hyperintensity observed on the initial MRI does not match the majority of published cases. Most of the consulted case reports and series indicate that neuroimaging is typically normal in the early stages or may reveal late cerebellar atrophy.3-12,14-17 However, Campana and Silva1 report that only 6% of patients present with MRI hyperintensity, which suggests a phase of acute inflammatory cerebellitis. Similar cases reported by Suri et al.18 and Avramova et al.13 show that these hyperintensities may resolve following treatment, although they often precede irreversible atrophy.
The presence of anarthria, bradyphrenia, and heteroaggression as presenting symptoms is unusual when compared with the literature. The involvement is typically limited to the cerebellum, as the DNER antigen is expressed almost exclusively in Purkinje cells in humans. Extracerebellar signs, such as encephalopathy, occur in only 8% of patients, according to the review by Campana and Silva.1
Immunotherapy strategies (high-dose corticosteroids, intravenous Igs, plasma exchange, and occasionally B cell-depleting therapies) have been used in anti-Tr/DNER PCD; however, reported neurological responses are overall limited and frequently incomplete.1 Consistently, reviews of paraneoplastic neurological syndromes in lymphoma emphasise that achieving tumour remission is the cornerstone of management, whereas immunotherapy adds variable and often modest benefit in classic onconeural antibody-associated syndromes.2
The persistence of anti-Tr antibody positivity after treatment, along with minimal neurological improvement, reveals some interesting findings. Bernal et al.3 documented that anti-Tr antibodies disappeared in 100% (10 out of 10) of patients who achieved tumour remission. However, this seronegativity does not usually translate into clinical improvement. As explained by Campana and Silva,1 and reinforced in the analysis by Arratibel et al.,12 the lack of recovery is attributed to the massive and irreversible destruction of Purkinje cells during the acute phase of the immune attack. A notable exception is the case reported by Peltola et al.,10 in which a tenfold reduction in antibody titres correlated with near-complete neurological recovery, emphasising the critical need for early intervention before irreversible neuronal damage occurs. The persistence of positive titres in the patient described in this report, despite complete oncological remission confirmed by CT, is a rarely described phenomenon. However, Geromin et al.17 observed that an increase in titres may precede nodal relapse, which requires close oncological follow-up in such cases.
This case reflects the tragic dichotomy described by Graus et al.2 in their 2014 review and in the case series by Hammack et al.:15 HL associated with anti-Tr antibodies is highly curable (with remission achieved in approximately 90% of cases), but neurological recovery remains exceptional. Only 14–41% of patients show significant improvement. As noted in the literature, this is due to the massive and irreversible destruction of Purkinje cells during the acute phase. Although ABVD treatment successfully eliminated the tumour’s immunogenic stimulus, the structural damage in the current patient’s cerebellum was already permanent.
In conclusion, this case highlights that anti-Tr/DNER PCD should be regarded as a neurological emergency in which time to diagnosis is critically important.
CONCLUSION
The diagnosis of subacute PCD often precedes the diagnosis of HL, which is also typically detected at a localised stage. This case highlights the importance of recognising atypical radiological and clinical features as potential indicators of paraneoplastic neurological syndromes. When treatment of the lymphoma results in complete remission, anti-Tr antibodies in serum usually become undetectable. However, among those who seroconvert, only a small percentage achieve neurological improvement, according to the literature. In this case, despite achieving complete remission on CT following chemotherapy for HL, anti-Tr antibodies remained positive and there was no neurological improvement.